Question:
Which of the following drugs is most commonly associated with causing Stevens-Johnson Syndrome (SJS)?
Which of the following drugs is most commonly associated with causing Stevens-Johnson Syndrome (SJS)?
Show Hint
Think about anticonvulsants and their association with severe cutaneous adverse reactions.
Updated On: Jun 23, 2026
- Lamotrigine
- Penicillin
- Aspirin
- Metformin
Show Solution

Verified By Collegedunia
The Correct Option is A
Solution and Explanation
Step 1: Identify drugs associated with Stevens-Johnson Syndrome (SJS).
SJS is a severe mucocutaneous hypersensitivity reaction with epidermal detachment affecting <10% of the body surface area. It is predominantly drug-induced.
Step 2: Key culprit drugs.
The most commonly implicated drugs include lamotrigine (most frequently cited anticonvulsant causing SJS, especially when dose is escalated rapidly or combined with valproate), carbamazepine (classic high-risk drug, especially in HLA-B*1502 carriers), phenytoin, allopurinol, sulfonamide antibiotics (co-trimoxazole), nevirapine, and oxicam-class NSAIDs.
Step 3: Eliminate distractors.
Penicillin causes urticaria and anaphylaxis more commonly than SJS. Aspirin is associated with GI adverse effects and Reye syndrome. Metformin is not associated with SJS.
Step 4: Mechanism.
SJS is mediated by cytotoxic T lymphocytes recognizing drug-peptide-MHC complexes, leading to keratinocyte apoptosis via Fas-FasL and granulysin pathways.
Answer: Lamotrigine
SJS is a severe mucocutaneous hypersensitivity reaction with epidermal detachment affecting <10% of the body surface area. It is predominantly drug-induced.
Step 2: Key culprit drugs.
The most commonly implicated drugs include lamotrigine (most frequently cited anticonvulsant causing SJS, especially when dose is escalated rapidly or combined with valproate), carbamazepine (classic high-risk drug, especially in HLA-B*1502 carriers), phenytoin, allopurinol, sulfonamide antibiotics (co-trimoxazole), nevirapine, and oxicam-class NSAIDs.
Step 3: Eliminate distractors.
Penicillin causes urticaria and anaphylaxis more commonly than SJS. Aspirin is associated with GI adverse effects and Reye syndrome. Metformin is not associated with SJS.
Step 4: Mechanism.
SJS is mediated by cytotoxic T lymphocytes recognizing drug-peptide-MHC complexes, leading to keratinocyte apoptosis via Fas-FasL and granulysin pathways.
Answer: Lamotrigine
Was this answer helpful?
0
0
Top NEET PG Pharmacology Questions
- A bronchial asthma patient on inhalational steroids presented with white patchy lesions on the tongue and buccal mucosa. What is the drug that can be used to treat this condition?
- A pregnant woman with a history of bronchial asthma is in the third stage of labor. Which drugs should be avoided in managing postpartum hemorrhage in this mother?
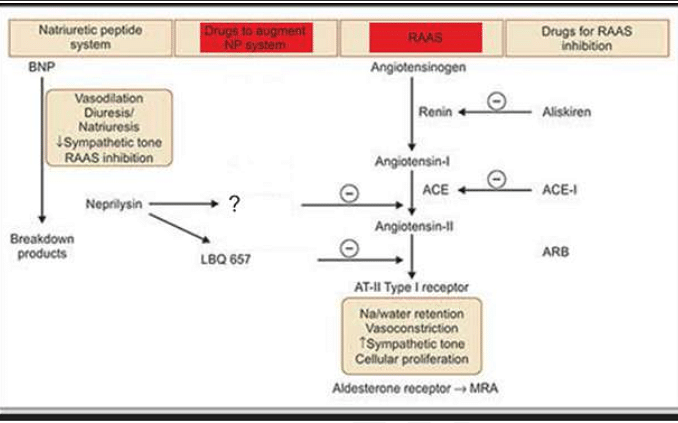
- Name the drug that acts on both the marked areas.
- A patient with a previous history of myocardial infarction and ventricular arrhythmia is ontreatment for a few months. He developed fatigue, dyspnea, and weight gain. He had also developed pulmonary fibrosis. Which of the following drugs is responsible for the side effects mentioned above?
- A young female comes to the emergency department after consuming 100 aspirin tablets.What should be the next step in management?
View More Questions
Top NEET PG Adverse Drug Reactions Questions
Top NEET PG Questions
- A patient hailing from Delhi presents with fever, arthralgia, and extensive petechial rash for 3 days. Lab investigations revealed a hemoglobin of 9 g/ dL, a white blood cell count of 9000 cells/mm3, a platelet count of 20000 cells/mm3, and a prolonged bleeding time. The clotting time was normal. What is the most likely diagnosis?
- Which of the following statements is true about Trichomonas vaginalis?
- A lady from West Rajasthan presented with an ulcer surrounded by erythema on the right leg. Microscopy of the biopsy from the edge of the ulcer showed organisms with dark staining nuclei and kinetoplast. What is the most likely causative agent?
- A child presents with a fever and a rash. Urine examination showed cells with owl's eye appearance. What is the most likely diagnosis?
- Infection with Clonorchis sinensis is associated with an increased risk of__?
View More Questions