Question:
Regarding PCOD (polycystic ovarian disease), all of the following are true except?
Regarding PCOD (polycystic ovarian disease), all of the following are true except?
Show Hint
A grossly raised level here would point you toward a prolactinoma instead.
Updated On: Jun 24, 2026
- High LH/FSH ratio
- High DHEAS
- Markedly high prolactin
- Raised LH
Show Solution

Verified By Collegedunia
The Correct Option is C
Solution and Explanation
Step 1: Recall the hormonal profile of PCOD. There is increased pulsatile GnRH leading to a raised LH and a reversed LH/FSH ratio (classically about 2:1 or more).
Step 2: Androgens are increased; adrenal androgen DHEAS is mildly to moderately elevated in a proportion of patients, and ovarian androgens (testosterone) are raised, producing hyperandrogenism.
Step 3: Consider prolactin. A mild elevation in prolactin can occasionally be seen, but a MARKEDLY high prolactin is not a feature of PCOD. A markedly raised prolactin points to a prolactinoma or other cause of hyperprolactinaemia, which is a separate differential. Therefore markedly high prolactin is the false statement.
Step 4: Hence the exception is markedly high prolactin.
Answer: Option C, Markedly high prolactin.
Step 2: Androgens are increased; adrenal androgen DHEAS is mildly to moderately elevated in a proportion of patients, and ovarian androgens (testosterone) are raised, producing hyperandrogenism.
Step 3: Consider prolactin. A mild elevation in prolactin can occasionally be seen, but a MARKEDLY high prolactin is not a feature of PCOD. A markedly raised prolactin points to a prolactinoma or other cause of hyperprolactinaemia, which is a separate differential. Therefore markedly high prolactin is the false statement.
Step 4: Hence the exception is markedly high prolactin.
Answer: Option C, Markedly high prolactin.
Was this answer helpful?
0
0
Top NEET PG Gynaecology and Obstetrics Questions
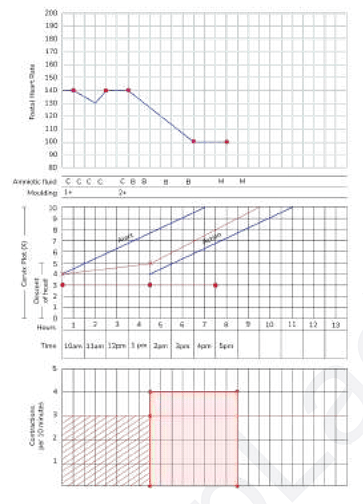
- A partogram of a woman who is in labor is shown below. Oxytocin infusion is already given. How will you manage the condition?
- A woman presents to you at 36 weeks of gestation with complaints of breathlessness and excessive abdominal distension. Fetal movements are normal. On examination, fetal parts are not easily felt and fetal heartbeat is heard but it is muffled. Her symphysis fundal height is 41 cm. Her abdomen is tense but not tender. What is the most likely diagonosis?
- For which of the following procedures in the given OT list, can you preferably do a hysteroscopy ?
- A primigravida presents to you with anemia early in her pregnancy. She is 7 weeks pregnant as seen on ultrasound. Her hemoglobin level is 9 g/dL. When should the iron supplements be started for her?
- A 23-year-old woman accompanied by her mother-in-law comes to the infertility clinic. She has been having regular intercourse for 6 months but is not able to conceive. What is the next best step?
View More Questions
Top NEET PG Questions
- A patient hailing from Delhi presents with fever, arthralgia, and extensive petechial rash for 3 days. Lab investigations revealed a hemoglobin of 9 g/ dL, a white blood cell count of 9000 cells/mm3, a platelet count of 20000 cells/mm3, and a prolonged bleeding time. The clotting time was normal. What is the most likely diagnosis?
- Which of the following statements is true about Trichomonas vaginalis?
- A lady from West Rajasthan presented with an ulcer surrounded by erythema on the right leg. Microscopy of the biopsy from the edge of the ulcer showed organisms with dark staining nuclei and kinetoplast. What is the most likely causative agent?
- A child presents with a fever and a rash. Urine examination showed cells with owl's eye appearance. What is the most likely diagnosis?
- Infection with Clonorchis sinensis is associated with an increased risk of__?
View More Questions